Pinched nerve in lower back · St. Louis
You can draw the line where it goes. That line is most of the diagnosis.
Lumbar radiculopathy, a pinched nerve in the lower back, means a lumbar nerve root is irritated or compressed. So the pain follows the territory of that root, and it brings numbness, tingling or weakness with it. The line your finger draws down your leg tells an examiner which level to look at. It does so before any scan is ordered.
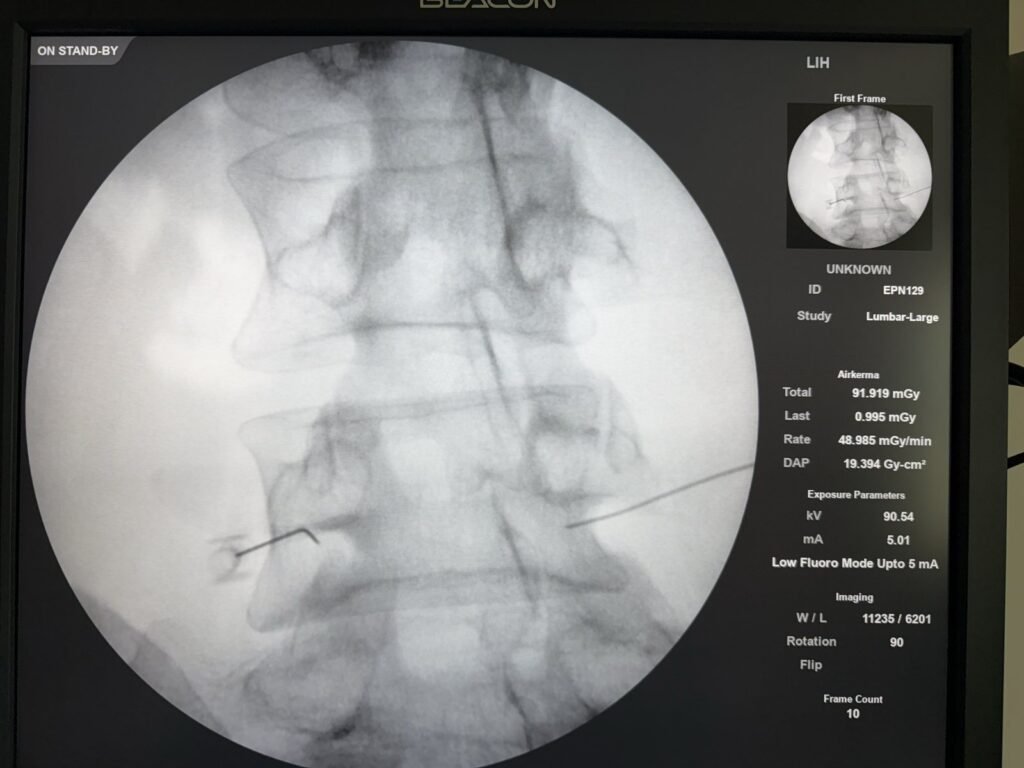
What is lumbar radiculopathy?
At each level, a nerve root leaves the spinal canal through a foramen (an opening between the bones). Anything that narrows that space or inflames what is inside it can make the root cause symptoms — a disc protrusion, a hypertrophied (enlarged) facet, a thickened ligament, a spondylolisthesis (one vertebra slipped forward on another). The result is radicular pain (pain that travels along the nerve). It feels different from the ache of a joint. It is sharper and electric, and it follows a path. It often comes with a genuine neurological finding.
It is worth being precise about a distinction that gets blurred. Radicular pain is pain made by an irritated root. Radiculopathy means the root is not conducting properly — numbness in a dermatome (a strip of skin), weakness in a myotome (a muscle group), a reduced reflex. You can have the first without the second. Having the second changes the urgency, and sometimes the treatment.
How can you tell which nerve root is pinched?
- L4 — pain across the front of the thigh into the inner shin, weak knee straightening, reduced knee reflex.
- L5 — down the outer thigh and shin into the top of the foot and the great toe. Weak lifting of the toes and ankle (dorsiflexion). This is the root behind a foot that slaps or catches.
- S1 — down the back of the thigh and calf into the outer foot and little toe. Weak push-off of the foot (plantar flexion) and a reduced ankle reflex. Trouble rising onto the toes on one side.
Those maps overlap between people. No textbook diagram is exact for any one person. Still, they are strong enough that a careful exam usually predicts the level the imaging will confirm. More usefully, it catches the cases where the imaging finding and the symptoms do not match.
The mismatch case is the important one. Say an MRI shows a protrusion at L4–5, but the symptoms follow S1. That scan is describing an incidental finding. Operating on it treats the picture instead of the patient. What your MRI actually showed.
Will lumbar radiculopathy go away on its own?
Most acute lumbar radiculopathy improves substantially over six to twelve weeks without surgery. A meaningful share of disc herniations resorb (get absorbed) on their own — the immune system treats pushed-out disc material as something to clear. That is the single most useful thing to know early. That is because it is the reason you should not make a decision you cannot undo in the first weeks, unless there is a reason to.
The reason to move faster is deficit (lost nerve function). Progressive weakness, a foot drop that is worsening, or any of the cauda equina findings change the calculation completely. That is because what is at risk is no longer comfort but function that does not come back. Pain is negotiable. A dying root is not.
How is lumbar radiculopathy treated?
- Examine and map. Dermatomes, myotomes, reflexes, straight leg raise and its crossed version, gait, and a heel and toe walk. The crossed straight leg raise is less sensitive and much more specific than the standard one. That makes it worth doing properly.
- Decide whether imaging changes anything. With no deficit and no red flag in the first weeks, usually it does not.
- Where the pain is severe or persistent, a targeted transforaminal epidural steroid injection at the level causing symptoms. It also helps diagnose, because relief at that level confirms the level.
- Reintroduce load deliberately rather than waiting for the pain to permit it. Nerve tissue handles graded (step-by-step) movement better than it handles staying still.
- Refer for a surgical opinion where there is a progressive deficit, or cauda equina. The same goes for a clearly located compression that has not settled and is disabling. That is a real reason for surgery, and we will say so.
Why does one person’s disc hurt and another’s does not?
Mechanical contact alone is a poor predictor of radicular pain. This is not a fringe finding — disc protrusions touching roots are found routinely in people with no symptoms at all. What makes contact painful is chemistry as much as shape. Pushed-out nucleus pulposus (the gel center of the disc) causes inflammation on its own. The inflammatory response around the root is what sensitizes it.
That inflammatory response is not set to the same volume in everyone. A nerve root places high demands on its tiny blood vessels (microcirculation). Chronic hyperinsulinemia (long-term high insulin) impairs blood flow through those vessels. At the same time, whole-body metabolic inflammation raises the baseline the local response starts from. In a body with metabolic inflammation, a smaller mechanical injury produces bigger and longer symptoms. Recovery runs slower, because the tissue is already in a state of breaking down.
The third driver is time and sleep. Weeks of severe nerve pain disrupt slow-wave (deep) sleep. Short sleep both raises inflammatory tone and lowers descending pain inhibition (the brain’s own pain brake). That is a loop. It is why a radiculopathy left to run for months so often stops behaving like a compression problem. It starts behaving like a sensitization problem — unchanged on imaging, worse in life.
Common questions
What are the first signs of L4-L5 compression?
Typically, pain down the outer thigh and shin toward the top of the foot, and tingling over the top of the foot and the great toe. There is also, typically, early weakness of toe extension — often noticed as catching a toe on a step rather than as weakness. Any of that which is progressing warrants prompt assessment rather than watchful waiting.
Where that weakness leads if it progresses is set out in foot drop.
Is walking good for nerve pain in the leg?
Generally yes, within tolerance. It is better than rest for both the nerve and the deconditioning (loss of fitness) that otherwise follows. If walking reliably brings on numbness or weakness that then takes time to clear, that is a different signal and should be assessed.
How painful is a herniated disc?
The honest answer is that it ranges from silent to among the more severe pains in medicine. The difference is driven more by inflammation and root sensitivity than by the size of the herniation. That is also why a large herniation on a report is not a prediction of how much someone hurts.
For why a herniation on a scan does not predict how much it hurts, read herniated disc or not.
Will I need surgery?
Most people with radiculopathy do not. Surgery has a clear role where there is progressive deficit or cauda equina. It also has a role for a clearly located compression that has failed to settle and is disabling. Where none of those applies, an operation is being asked to solve a problem that is likely to clear up on its own schedule. Before you agree to the operation.
Does an epidural cure it?
It does not resorb the disc. What it does is reduce the inflammation around the root. That frequently reduces the pain enough to let the natural course proceed and to let you move again. Where it works well, it also confirms the level, which is worth having.
What is the difference between lumbar radiculopathy and sciatica?
Sciatica is the everyday word for pain running down the leg. Radicular pain is pain made by an irritated lumbar nerve root. It is sharper and more electric than a joint ache. Radiculopathy goes a step further: the root is not conducting properly. So there is numbness in a strip of skin, weakness in a muscle group or a reduced reflex. You can have the pain without the radiculopathy.
What activities should you avoid with lumbar radiculopathy?
Long stretches of rest are the main thing to avoid. Nerve tissue handles graded movement better than it handles immobility. Walking within tolerance is generally better than lying down. Load is brought back deliberately rather than waiting for the pain to allow it. If walking reliably brings on numbness or weakness that takes time to clear, stop and get it assessed.
Can a pinched nerve be seen on an MRI?
An MRI can show a disc or bone narrowing the space around a root. But contact alone does not prove it is the cause. Disc protrusions touching nerve roots show up routinely in people with no symptoms. The exam usually predicts the level a scan will confirm. It also catches the cases where the picture and the symptoms do not match.
When is lumbar radiculopathy an emergency?
When the nerve is losing function, not just hurting. Progressive weakness, a foot drop that is getting worse, or any cauda equina finding changes the plan completely. That is because what is at risk is function that may not come back. Those findings call for prompt assessment and a surgical opinion rather than waiting to see if it settles.
Can a chiropractor fix a pinched nerve in the lower back?
Manipulation does not push disc material back off a nerve root. The pressure on the root comes from extruded disc and the inflammation around it, and that clears by resorption over weeks, not by moving a joint. Manual therapy can ease the stiff, guarded back that comes along with it, and plenty of people find that worth having. If numbness or weakness in the leg is getting worse, pause the adjustments and get the root examined, because a foot that starts to catch on stairs is where an L5 root left too long ends up. How a herniation clears on its own explains the timeline.
Do I need a referral for a pinched nerve in my lower back?
No. You can book directly; some insurance plans want a referral on file, so check yours. Tell us right away if the leg is getting weaker or a foot is catching, because that changes the timeline. How an epidural reaches the inflamed root.
If testing is needed to confirm which root is pinched, our page on the EMG nerve test for sciatica explains how the leg nerves are checked and how to get ready.
Related reading
- Epidural steroid injection
- Is it actually the disc?
- Sciatica, and what impersonates it
- When back pain is an emergency
- Before you agree to the operation
Not every leg symptom is a nerve root. Piriformis syndrome is a diagnosis of exclusion that gets handed out first.
Draw us the line, and tell us what is weak
Those two pieces of information do more to localize a radiculopathy than most of what happens in a scanner. Bring any imaging you already have and we will tell you whether it matches your symptoms.
12174 Natural Bridge Rd, Suite 301
St. Louis, MO 63044
At DePaul Hospital on Natural Bridge Road, inside the I-270 and I-70 interchange, on the west side of the airport.
Sources
- van der Windt DA et al. Physical examination for lumbar radiculopathy due to disc herniation in patients with low-back pain. The Cochrane database of systematic reviews, 2010. PubMed 20166095
- Stochkendahl MJ et al. National Clinical Guidelines for non-surgical treatment of patients with recent onset low back pain or lumbar radiculopathy. European spine journal : official publication of the European Spine Society, the European Spinal Deformity Society, and the European Section of the Cervical Spine Research Society, 2018. PubMed 28429142
- Berry JA et al. A Review of Lumbar Radiculopathy, Diagnosis, and Treatment. Cureus, 2019. PubMed 31788391
- Dar KH et al. Nonsurgical versus surgical treatment for cervical radiculopathy: a systematic review and meta-analysis of randomized controlled trials. European journal of orthopaedic surgery & traumatology : orthopedie traumatologie, 2026. PubMed 42029974