Lumbar radiofrequency ablation · St. Louis
Durable relief for facet pain, if the right nerves were identified first.
Lumbar radiofrequency ablation, also called radiofrequency neurotomy, interrupts the small nerves that carry pain from a facet joint. It works well in patients whose facets were confirmed by block. It works poorly in patients picked any other way. Almost everything about its reputation comes down to that one sentence.
What is lumbar radiofrequency ablation?
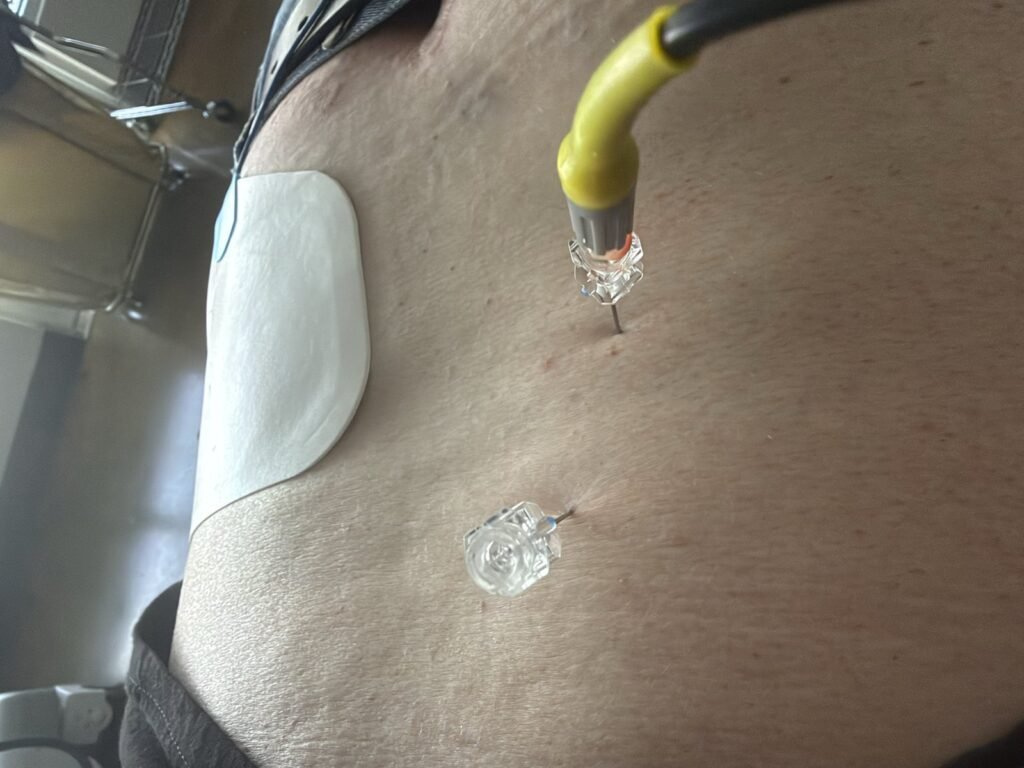
A special needle with an insulated shaft and an active tip is placed along the path of a medial branch nerve. Fluoroscopy (live X‑ray) guides it. Radiofrequency current heats the tip, and the heat makes a small, controlled lesion in the nerve. The nerve stops carrying signals, and the joint it served stops reporting pain.
The placement is different from a block, and it is worth understanding because it explains why technique matters. A block only needs the anesthetic to reach the nerve, so a needle near it will do. A lesion has to physically wrap around the nerve. So the needle is laid parallel along its path, not placed at a right angle to it. Sensory and motor stimulation are used before lesioning. They confirm the tip is on the right nerve and not on a nerve root.
Who is a good candidate for radiofrequency ablation?
The selection rule is not complicated, and it is often ignored. It is patients whose facet-mediated pain has been confirmed by diagnostic medial branch blocks, preferably two. When that is the standard, outcomes are good and durable. When patients are picked on imaging findings or a clinical hunch, outcomes are poor. The published literature contains both groups. That is a large part of why the evidence looks inconsistent when read casually.
So you may have read that radiofrequency ablation for back pain does not work. The more precise version is that it does not work when it is done to the wrong people. That is a selection problem, not a technology problem, and it can be fixed at the point of diagnosis.
What happens during radiofrequency ablation, and how long is recovery?
- Face down, skin cleaned and numbed, needles placed under live fluoroscopy along each target nerve. Usually several per side.
- Stimulation testing. You will be asked what you feel. A tingle in the back is expected. A feeling shooting down the leg is not, and it means the needle moves before anything is heated.
- More local anesthetic, then the lesions. Each takes a couple of minutes. You may feel warmth or a deep ache while it runs.
- Soreness for one to two weeks. This part is routinely under-explained. It is the most common reason people think the procedure failed. The area you just had treated is sore, and a burning or sunburned feeling over the skin is common.
- Relief builds over two to six weeks as that settles. Judging the result at day three is judging the soreness, not the outcome.
Do not judge this procedure early. A significant number of people decide it did not work during the sore stretch after the procedure. They never come back for a result that was on its way.
How long does radiofrequency ablation last?
The nerves regenerate. That is not a failure of the procedure; it is a property of nerves. The effect typically lasts many months before symptoms return as the medial branches recover. When they do, the procedure can be repeated. A patient who responded well the first time generally responds again to a repeat.
The medial branches are sensory: they carry feeling from the joint. Because of that, interrupting them does not cause weakness. But a joint that no longer reports load is a joint you can overload without warning. That is one reason the conditioning work alongside it is not optional.
What the procedure does not do
It does not repair the joint. It does not change the mechanics that overloaded it. It does not address why the tissue failed. It removes the signal. That is truly valuable — a person in less pain moves more, sleeps better and reconditions. But it is a window, not a cure.
What fills the window is the treatment. Rebuild the extensor (back) and gluteal muscle so the passive structures carry less load. Restore tolerance for extension (leaning back), rather than avoiding it forever. Restore sleep, because that is when connective tissue actually renews itself. And address the metabolic terrain. That is because glycated (sugar-damaged), chronically inflamed collagen fails again under the same load that failed it the first time.
That behavioral and lifestyle work is roughly 40 to 50 percent of the protocol here. The Acceptance and Commitment Therapy part is delivered in-house, not referred out. A neurotomy without it buys you a quieter year. A neurotomy with it changes what happens after the nerves grow back.
What are the risks of radiofrequency ablation?
Soreness for one to two weeks after the procedure is expected, not a complication. Temporary numbness over the skin of the back is common. A small share of patients develop a neuritic (nerve-irritation) burning that settles over weeks. Bleeding, infection and injury to a nerve root are uncommon. Stimulation testing before lesioning is there specifically to reduce the last of those. No steroid is used.
Frequently asked questions
Is radiofrequency ablation permanent?
No, and it is designed not to be. The nerves regrow, the effect fades, and the procedure is repeated if it helped. A permanent destructive lesion would be a far bigger commitment, with far more ways to go wrong.
Related: lumbar medial branch block.
How soon will I know if it worked?
Two to six weeks. Anything you feel in the first week is mostly the procedure, not the result.
The block that should come first is covered in lumbar medial branch block.
Will it weaken my back?
Not directly — the medial branches are sensory (they carry feeling). There is evidence of some atrophy (shrinking) in the small multifidus muscles they also supply. That is one more reason the strengthening work afterward matters, and why it is prescribed rather than suggested.
Related: lumbar facet syndrome.
Can I have it again?
Yes, once symptoms return as the nerves regenerate. Response to a repeat is usually similar to the first.
The condition it treats is covered in lumbar facet syndrome.
Why did mine not work last time?
There are three usual reasons. The diagnosis was never confirmed by block. Or the lesion did not capture the nerve because of the needle angle. Or it was judged during the sore stretch. All three are worth going through before deciding the procedure is not for you.
Confirming the diagnosis first is the subject of lumbar medial branch block.
What is the success rate of radiofrequency ablation for back pain?
It depends almost entirely on who is selected. When facet pain has first been confirmed by diagnostic medial branch blocks, preferably two, outcomes are good and durable. When patients are picked on imaging findings or a clinical hunch, outcomes are poor. The published studies mix both groups. That is why the overall evidence looks inconsistent. If your facets have not been confirmed, we start with the block.
Are you put to sleep during radiofrequency ablation?
No. You lie face down, and the skin is cleaned and numbed with local anesthetic. More local anesthetic is given before each lesion. You need to be awake for the stimulation test. A tingle in the back is expected. Anything shooting down the leg means the needle is moved before any heat is applied. You may feel warmth or a deep ache while each lesion runs.
What conditions does lumbar radiofrequency ablation treat?
It treats facet joint pain in the lower back, also called lumbar facet syndrome. The heat makes a small lesion in the medial branch nerves that carry pain from the facet joints. So the joint stops reporting pain. It works when a medial branch block has already confirmed the facet joints as the source. It does not repair the joint; it removes the pain signal.
What is the downside of radiofrequency ablation?
The relief is temporary by design. The nerves regrow and symptoms return after many months, though the procedure can be repeated. Expect one to two weeks of soreness, sometimes with a sunburned feeling over the skin. And because the joint no longer reports load, you can overload it without warning. That is why strengthening work afterward is prescribed rather than optional.
Related reading
- The diagnostic block, explained
- Lumbar facet syndrome
- Pain after back surgery
- Sleep and back pain
- What happens at the first visit
The procedure is straightforward. The selection is the hard part.
If your facets have been confirmed, this is a durable answer. If they have not, we will start there rather than proceeding on a hunch.
12174 Natural Bridge Rd, Suite 301
St. Louis, MO 63044
At DePaul Hospital on Natural Bridge Road, inside the I-270 and I-70 interchange, on the west side of the airport.
Sources
- Park S et al. Radiofrequency treatments for lumbar facet joint syndrome: a systematic review and network meta-analysis. Regional anesthesia and pain medicine, 2025. PubMed 39481876
- Láinez Ramos-Bossini AJ et al. Efficacy of radiofrequency in lumbar facet joint pain: a systematic review and meta-analysis of placebo-controlled randomized controlled trials. La Radiologia medica, 2024. PubMed 38512629
- Chen CH et al. Radiofrequency neurotomy in chronic lumbar and sacroiliac joint pain: A meta-analysis. Medicine, 2019. PubMed 31261580
- Tieppo Francio V et al. Multifidus atrophy and/or dysfunction following lumbar radiofrequency ablation: A systematic review. PM & R : the journal of injury, function, and rehabilitation, 2024. PubMed 38757474